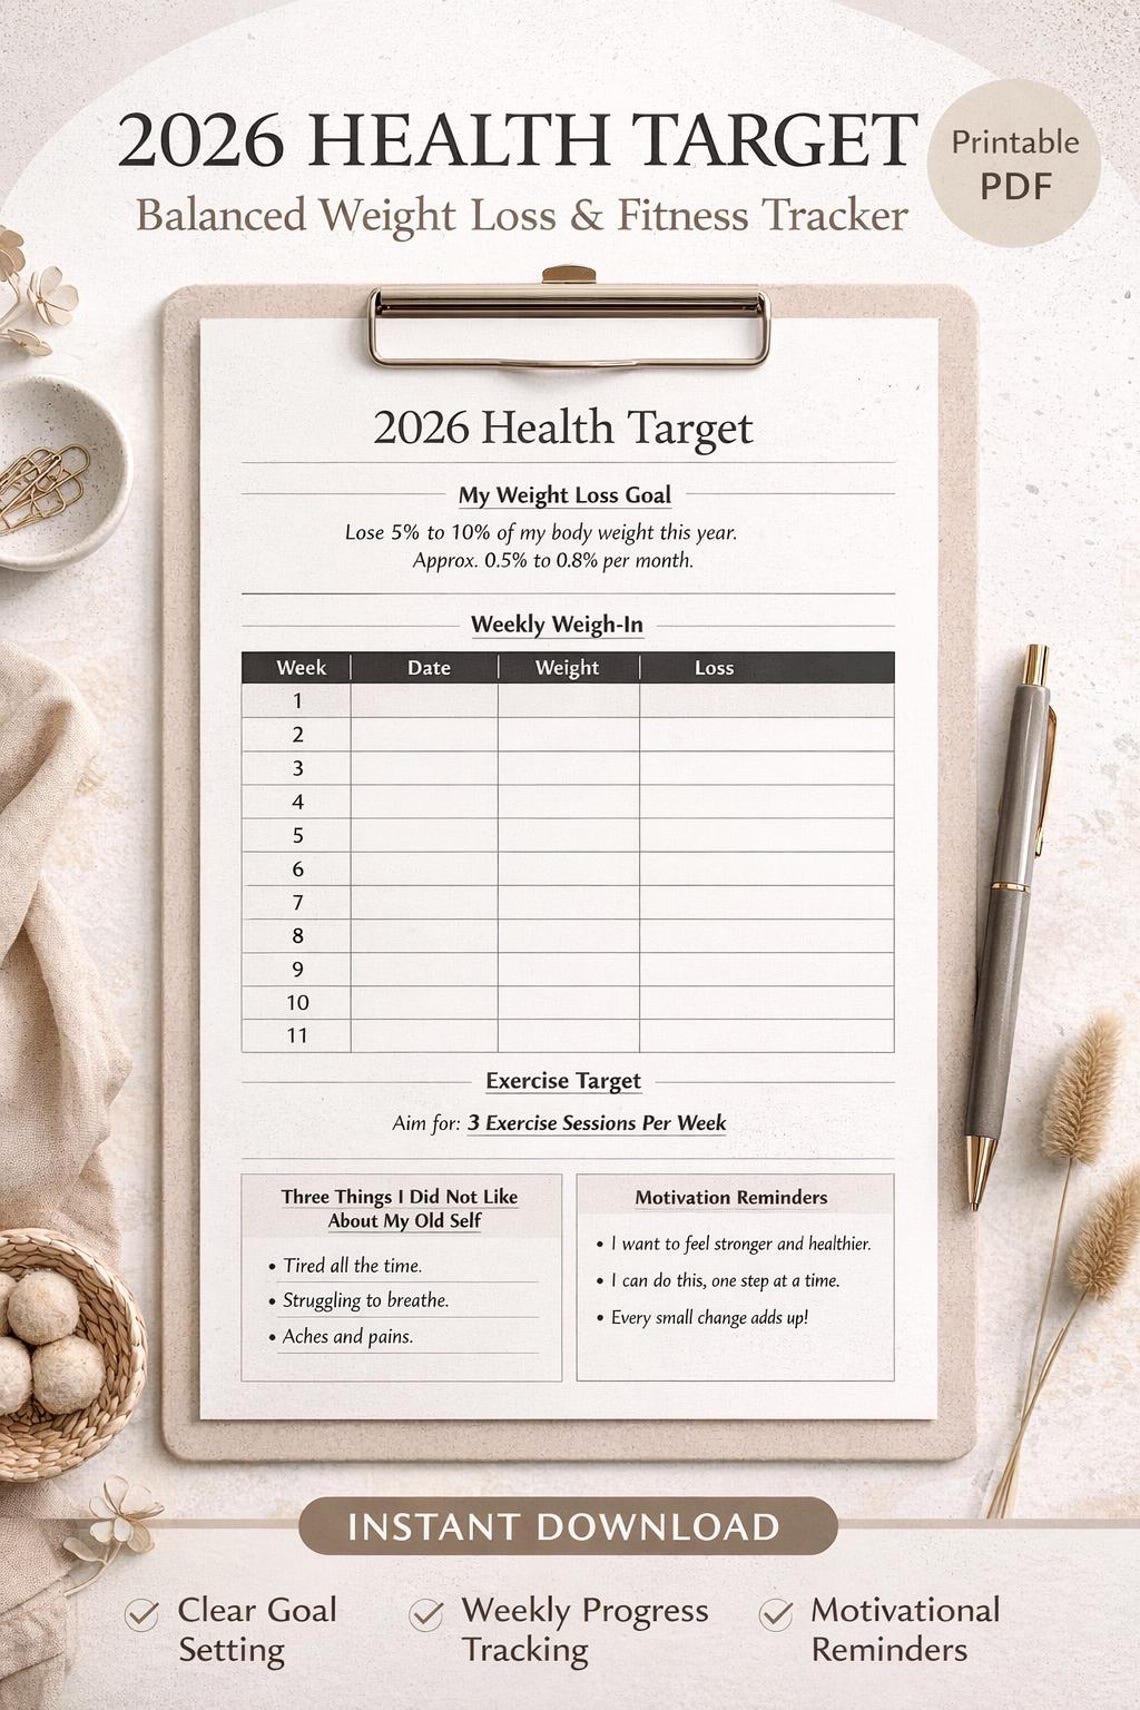
A modern weight loss journey in 2026 combines personalized nutrition, resistance training, behavioral psychology, and clinical guidance rather than relying on extreme calorie restriction. By prioritizing lean muscle preservation, metabolic health, and sustainable habit formation, individuals can achieve long-term fat loss while improving overall cardiovascular and metabolic biomarkers.
Disclaimer: The information provided in this guide is for educational purposes only and does not constitute medical advice. Individuals should consult a qualified healthcare provider or registered dietitian before starting any significant dietary, exercise, or medical weight management program.
The Modern Paradigm of Weight Loss and Metabolic Health
The approach to weight management has evolved significantly. Historical weight loss attempts frequently relied on severe caloric restriction, elimination diets, or unmonitored cardiovascular exhaustion. While these methods often yielded rapid initial reductions on the bathroom scale, they routinely failed over long horizons due to muscle loss, severe metabolic adaptation, and intense psychological fatigue.
In 2026, scientific consensus emphasizes fat loss over mere weight reduction, highlighting the crucial distinction between losing adipose tissue and losing lean muscle body mass. Preserving lean muscle tissue is essential for maintaining Basal Metabolic Rate (BMR), supporting functional mobility, and optimizing glucose disposal. Modern approaches view body composition management through the lens of overall metabolic health—incorporating blood lipid profiles, insulin sensitivity, sleep architecture, and stress management alongside body weight metrics.
Furthermore, the widespread clinical integration of metabolic pharmacotherapy—such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) receptor agonists—has altered how individuals and clinicians approach weight loss. When prescribed under medical supervision, these treatments serve as powerful adjuncts to lifestyle modifications. However, clinical literature from bodies such as the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) emphasizes that medical treatments must be paired with structured strength training and high-protein nutrition to prevent substantial loss of skeletal muscle mass and bone mineral density.
Core Pillars of Evidence-Based Weight Loss
Achieving long-term fat loss requires balancing several interconnected biological and behavioral factors. Focusing on a single element—such as caloric reduction—without supporting physical training or sleep hygiene often leads to early plateaus and weight regain.
| SUSTAINABLE WEIGHT LOSS PILLARS |
|---|
| 1. Energy Balance & High-Protein Nutrition |
| 2. Progressive Resistance Training & Daily Physical Activity |
| 3. Restorative Sleep Architecture & Stress Management |
| 4. Behavioral Psychology & Habit Formation |
Energy Balance, Protein Leverage, and Micronutrient Quality
Energy balance remains the fundamental physical law governing body mass change. To reduce body fat, an individual must maintain a persistent, moderate energy deficit, where total energy expenditure exceeds total caloric intake. However, the composition of calories matters greatly for metabolic health and satiety.
- Protein Leverage: Consuming adequate dietary protein (typically 1.6 to 2.2 grams per kilogram of total body weight daily) helps preserve muscle tissue during a caloric deficit. Protein also exhibits the highest thermic effect of food (TEF)—requiring up to 30% of its ingested calories simply for digestion and processing—and stimulates satiety hormones like peptide YY (PYY) and GLP-1 naturally.
- Micronutrient Satiety: Whole, minimally processed foods deliver high nutrient volume per calorie. Prioritizing dietary fiber (25–38 grams daily from vegetables, legumes, and whole grains) delays gastric emptying, stabilizing blood glucose spikes and reducing hunger pangs.
Resistance Training and Physical Activity Architecture
Physical activity during a weight loss journey is best divided into structured exercise and daily non-exercise activity:
- Progressive Resistance Training (PRT): Lifting weights or engaging in bodyweight resistance exercises at least two to four times per week provides the mechanical stimulus necessary to signal the body to retain muscle mass. Without resistance stimulus, a caloric deficit forces the body to break down both adipose tissue and skeletal muscle for fuel.
- Non-Exercise Activity Thermogenesis (NEAT): NEAT encompasses all physical movement that is not structured exercise, including walking, standing, household chores, and fidgeting. NEAT accounts for a significantly larger portion of daily caloric expenditure than structured workouts. Increasing daily step counts (targeting 7,000–10,000 steps daily) helps maintain overall energy expenditure without inducing the intense appetite surges often triggered by excessive high-intensity cardio.
Sleep Hygiene, Stress Regulation, and Hormones
Chronic sleep deprivation and elevated psychosocial stress can undermine weight loss progress through neuroendocrine dysregulation:
- Ghrelin and Leptin: Insufficient sleep (less than 7 hours per night) elevates ghrelin (the hunger hormone) and suppresses leptin (the satiety hormone). This imbalance dramatically increases cravings for energy-dense, hyper-palatable foods high in sugar and fats.
- Cortisol Management: Sustained high levels of the stress hormone cortisol promote fluid retention, obscure body weight measurements, and encourage visceral fat deposition around abdominal organs. Prioritizing structured sleep hygiene and mindfulness practices directly supports metabolic stability.
A Step-by-Step Roadmap for Your 2026 Journey
Structuring a weight loss plan into distinct phases improves adherence and provides clear benchmarks for tracking progress over time.
- Phase 1: Baseline Assessment & Diagnostics
- Phase 2: Nutrition & Exercise Blueprint Setup
- Phase 3: Active Fat Loss Execution & Monitoring
- Phase 4: Managing Plateaus & Adjusting Targets
- Phase 5: Transition to Long-Term Maintenance
Step 1: Establish Initial Baselines and Biomarkers
Before altering nutritional intake or exercise habits, establish precise baseline data:
- Clinical Blood Panel: Request comprehensive diagnostics from a healthcare provider, including fasting lipid profiles, HbA1c, fasting insulin, thyroid function panels (TSH, free T3/T4), and vitamin D levels.
- Body Composition Metrics: Rather than relying solely on body mass index (BMI) or standard bathroom scales, obtain baseline measurements using dual-energy X-ray absorptiometry (DEXA), bioelectrical impedance analysis (BIA), or consistent waist-to-hip ratio measurements.
- Dietary Logging Baseline: Log standard dietary habits for 7 to 10 days without attempting to restrict calories. This establishes an accurate picture of actual baseline intake, habitual timing, and emotional eating patterns.
Step 2: Calculate Energy Requirements and Macronutrient Splits
To set realistic goals, calculate Total Daily Energy Expenditure (TDEE), which combines Basal Metabolic Rate (BMR) with daily movement and exercise.
- Determine Maintenance: Calculate estimated TDEE using established equations such as the Mifflin-St Jeor formula, adjusted for activity level.
- Establish Deficit: Subtract 300 to 500 kcal per day from the estimated TDEE. This mild-to-moderate deficit targets a safe, sustainable fat loss rate of roughly 0.5% to 1% of total body weight per week, minimizing muscle loss and fatigue.
- Distribute Macronutrients:
- Protein: 1.6 to 2.2 g per kg of body weight.
- Fats: 20% to 35% of total caloric intake, focusing on monounsaturated and polyunsaturated fatty acids.
- Carbohydrate: Fill remaining calories with complex carbohydrates to fuel training performance and maintain glycogen stores.
Step 3: Implement Habit Stacking and Behavioral Tracking
Attempting to overhaul all daily habits simultaneously frequently leads to burnout. Use habit stacking—anchoring a new behavior to an established daily routine:
- Example: "After I pour my morning coffee (established habit), I will drink a 16-ounce glass of water and complete a 5-minute movement routine (new habit)."
- Track progress using multiple metrics: weekly average body weight, body circumference measurements, progress photos taken under consistent lighting, energy levels, and gym strength metrics.
Step 4: Navigating Weight Loss Plateaus
A weight loss plateau occurs when scale weight remains unchanged for 3 to 4 consecutive weeks despite reported adherence to a plan. Plateaus are a natural biological response caused by metabolic adaptation—the body slowing certain processes to conserve energy as it grows smaller.
To systematically troubleshoot a plateau:
- Verify Tracking Accuracy: Re-weigh food portions using a digital scale for several days to catch subtle intake increases or uncounted liquid calories.
- Assess NEAT Variations: Unconscious drops in physical movement (e.g., sitting more due to minor fatigue) can reduce daily energy expenditure by several hundred calories. Monitor step counts closely.
- Implement a Diet Break: Introduce a 1- to 2-week period at estimated maintenance calories, keeping protein high while increasing carbohydrates. Diet breaks help alleviate psychological fatigue, restore circulating leptin levels, and reduce stress-induced fluid retention.
- Adjust Energy Targets: If adherence is confirmed and NEAT is high, reduce daily intake by an additional 100 to 200 calories or add 1,500 daily steps to restore the target energy deficit.
Step 5: Transitioning to Long-Term Weight Maintenance
Ending a active weight loss phase requires a deliberate strategy to prevent rapid weight regain. The transition phase shifts focus from losing mass to solidifying metabolic stability:
- Reverse Dieting: Gradually increase daily caloric intake by 100 to 150 calories every 1 to 2 weeks until reaching new maintenance energy levels. This allows the metabolic rate to adjust while rebuilding depleted glycogen and muscular reserves.
- Establish Flexible Ranges: Transition from strict body weight targets to a maintenance band (e.g., maintaining within a 5-pound window). Small fluctuations due to water retention, sodium shifts, or digestive volume are normal and should not trigger restrictive dieting cycles.
Comparative Evaluation of Weight Management Strategies
Selecting an approach depends on individual medical history, daily lifestyle, preferences, and long-term sustainability goals. The table below compares common approaches utilized in 2026.
| Strategy | Primary Mechanism | Best Suited For | Muscle Preservation Potential | Key Risks / Considerations |
|---|---|---|---|---|
| High-Protein Caloric Restriction | Moderate energy deficit with high protein ratio (1.6–2.2g/kg) and progressive weight training. | Individuals seeking sustainable, long-term body re-composition without eliminating food groups. | High (When paired with resistance exercise) | Requires consistent dietary logging and patience; initial weight loss is steady rather than rapid. |
| Medically Assisted Protocols (GLP-1/GIP Agonists under clinical oversight) | Pharmacological appetite suppression and delayed gastric emptying. | Individuals with clinical obesity (BMI ≥30) or metabolic co-morbidities under physician management. | Moderate to Low (Requires strict protein/resistance intervention) | GI side effects; elevated risk of lean tissue loss if protein and strength training are neglected; requires medical monitoring. |
| Time-Restricted Feeding (Intermittent Fasting, e.g., 16:8 window) | Restricting eating to a specific daily window to lower total caloric intake passively. | Busy schedules, individuals who prefer larger, fewer meals and do not struggle with hypoglycemia. | Moderate | Potential difficulty meeting daily high-protein targets in shorter eating windows; may cause overeating in some individuals. |
| Very Low-Carbohydrate / Ketogenic | Severe carbohydrate restriction (<50g/day) shifting fuel utilization toward ketone bodies. | Individuals with marked insulin resistance or specific medical indications under professional supervision. | Moderate | Initial fluid/electrolyte shifts; adherence can be difficult socially; requires careful lipid profile monitoring. |
Common Pitfalls and How to Avoid Them
Even well-designed weight loss plans can be derailed by common missteps. Identifying these issues early helps ensure long-term progress.
Excessive Muscle Wasting (Sarcopenic Weight Loss)
Losing weight too quickly (exceeding 1.5% of total body weight per week) or omitting resistance training leads to significant lean tissue loss. Muscle loss reduces resting metabolic rate, making long-term weight maintenance difficult and increasing the risk of weight regain (relapse).
- Prevention: Keep calorie deficits moderate, consume high-protein meals distributed across 3 to 4 daily feedings, and maintain progressive overload in resistance training routines.
Overestimating Exercise Caloric Burn
Wearable fitness trackers often overestimate calories burned during workouts by 15% to 30%. Relying on device readouts to consume additional calories often eliminates the targeted deficit entirely.
- Prevention: Treat exercise primarily as a tool for cardiovascular conditioning and muscle retention rather than an energy-offset mechanism. Calculate target caloric intake based on baseline TDEE equations rather than dynamically adding back estimated exercise calories.
Neglecting Sleep and Stress Management
Focusing exclusively on food and exercise while ignoring elevated chronic stress and poor sleep schedules often leads to persistent fluid retention caused by elevated cortisol. This fluid can mask body fat reduction on the scale, inducing frustration and prompting unnecessary, severe food restriction.
- Prevention: Maintain consistent sleep and wake times, limit late-night screen exposure, and track non-scale indicators of progress (such as strength levels, waist measurements, and daily energy).
Frequently Asked Questions
How fast should I expect to lose weight safely?
A safe and sustainable rate of fat loss is generally 0.5% to 1% of your total body weight per week. For a 180-pound individual, this equates to roughly 0.9 to 1.8 pounds per week. Losing weight at this steady pace preserves lean skeletal muscle tissue, minimizes adaptive thermogenesis, and makes long-term maintenance significantly easier.
Are GLP-1 medications necessary for weight loss in 2026?
No, GLP-1 and GIP medications are not necessary for everyone. They are specific clinical tools designed for individuals with obesity or related metabolic conditions under medical supervision. Sustainable weight loss can be fully achieved through lifestyle intervention—including a consistent caloric deficit, protein prioritizing, and structured resistance exercise. Anyone considering weight loss medications should consult a healthcare professional to evaluate personal medical necessity, potential risks, and required lifestyle pairing.
What should I do if my weight loss stalls for several weeks?
First, verify your tracking precision by using a food scale to weigh portions for several days, including cooking oils, dressings, and snacks. Second, check your daily step count to ensure your non-exercise activity (NEAT) hasn't unconsciously dropped. If tracking accuracy and activity levels are verified and scale weight remains unchanged for over three weeks, consider implementing a 1-week diet break at maintenance calories or reducing your daily intake by 100 to 200 calories.
How much protein do I really need while losing fat?
To preserve lean muscle mass during a caloric deficit, aim for 1.6 to 2.2 grams of protein per kilogram of body weight daily (approximately 0.7 to 1.0 grams per pound). Spreading this intake across three to four balanced meals throughout the day helps maximize muscle protein synthesis and keeps satiety levels high.
Can I lose body fat while building muscle at the same time?
Yes, body recomposition—losing fat while gaining muscle—is achievable, particularly for beginners to resistance training, individuals returning from a long training layoff, or those carrying higher amounts of body fat. Achieving this requires keeping your caloric deficit mild (200–300 kcal/day), consuming high daily protein, and consistently challenging your muscles through progressive resistance training.
Actionable Next Steps
To build a sustainable weight loss plan, focus on immediate, measurable actions:
- Schedule Baseline Diagnostics: Visit a primary care physician to obtain current metabolic blood markers and review any proposed dietary changes or pharmacotherapy options.
- Establish True Baseline Intake: Track your typical food intake for seven days using a nutrition tracking app without altering your normal diet, establishing your true starting point.
- Incorporate Resistance Training: Commit to a two- to three-day per week full-body strength training program focused on foundational compound movements (squats, presses, rows, hinges).
- Prioritize Daily Movement: Set a baseline step count target tailored to your current habits (e.g., adding 1,500 daily steps to your current average) to support consistent daily energy expenditure.
- Focus on Habit Consistency: Choose one nutritional habit—such as hitting a daily protein target—and maintain it consistently for three weeks before introducing additional restrictive changes.
For further evidence-based guidelines on healthy weight management, visit the Centers for Disease Control and Prevention (CDC) Healthy Weight Resource.